


Page 54 - Read Online
P. 54
Page 457   Goyal et al. Art Int Surg. 2025;5:450-64   https://dx.doi.org/10.20517/ais.2024.108


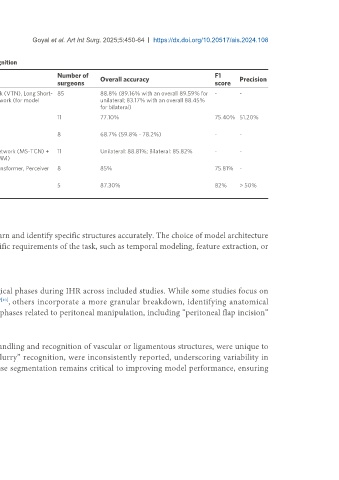
 Table 3. Comparison of AI models, annotation tools, and accuracy metrics for surgical phase recognition

                     Number of                                              F1
 Authors  Annotation software  AI model type  Model architecture  Overall accuracy   Precision
                     surgeons                                               score
 Ortenzi et al.   Manual annotation  Surgical Intelligence Platform   Video Transformer Network (VTN), Long Short- 85  88.8% (89.16% with an overall 89.59% for  -  -
 [10]
 (2023)  (Theator Software Co.)  Term Memory (LSTM) network (for model   unilateral; 83.17% with an overall 88.45%
 adaptation)                        for bilateral)
 Takeuchi et al.   CVAT (Computer Vision  DETR (Detection Transformer)  -  11  77.10%  75.40% 51.20%
 [20]
 (2023)  Annotation Tool)
 Choksi et al.   Manual annotation  ResNet-50 (Microsoft   -  8  68.7% (59.8% - 78.2%)  -  -
 [21]
 (2023)  Research)
 Takeuchi et al.   Indexiv Annotation   TeCNO (Transsion Holdings) &  Temporal Convolutional Network (MS-TCN) +   11  Unilateral: 88.81%; Bilateral: 85.82%  -  -
 [8]
 (2022)  Platform  Hidden Markov Model (HMM)  Hidden Markov Model (HMM)
 Zang et al.   Manual annotation  CV/DL  ResNet-50, Video Swin Transformer, Perceiver   8  85%  75.81%  -
 [9]
 (2023)  IO
 Zygomalas et al.  SuperAnnotate v1.1.0  YOLOv8 (Ultralytics Inc.)  -  5  87.30%  82%  > 50%
 [7]
 (2024)

 AI: Artificial intelligence.


 These models were trained using annotated datasets, allowing the systems to learn and identify specific structures accurately. The choice of model architecture

 was influenced by the nature of the input data (videos or images) and the specific requirements of the task, such as temporal modeling, feature extraction, or
 real-time analysis.


 Surgical phase recognition

 Significant heterogeneity exists in the identification and classification of surgical phases during IHR across included studies. While some studies focus on
 broad procedural steps such as “balloon dissection” and “mesh placement” , others incorporate a more granular breakdown, identifying anatomical
  [10]
 landmarks like the “pubic symphysis” and “iliopsoas muscle” . Additionally, phases related to peritoneal manipulation, including “peritoneal flap incision”
 [20]
 and “closure,” were emphasized in works by Takeuchi et al.  and Zang et al. .
 [9]
 [8]

 Notably, certain steps critical to surgical workflows, such as “needleholder” handling and recognition of vascular or ligamentous structures, were unique to
 specific models . Late procedural phases, including “stationary idle” and “blurry” recognition, were inconsistently reported, underscoring variability in
 [7]
 endpoint definition [Table 4]. Establishing a standardized framework for phase segmentation remains critical to improving model performance, ensuring
 comparability, and advancing automation in inguinal hernia surgery.

